Coronary Thrombosis Explained: Causes, Warning Signs, and Recovery
Coronary Thrombosis: What Happens During a Heart Attack (And How to Spot the Warning Signs)
Table of Contents
Coronary thrombosis is the medical term for a blood clot that blocks one of the arteries feeding your heart. It’s the single most common cause of a heart attack. This isn’t just “a clot forms and blocks things”, there’s a specific, well-understood sequence of events inside your body, and knowing the details actually helps you understand why symptoms happen, why treatment works the way it does, and why some risk factors matter more than others.
What Is Coronary Thrombosis, Exactly?
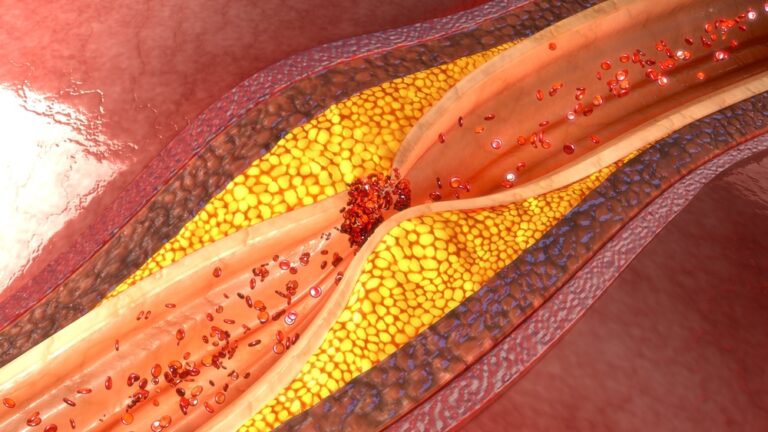
Your heart has its own small network of coronary arteries that keep the heart muscle supplied with oxygen-rich blood. Coronary thrombosis happens when a blood clot forms inside one of these arteries and blocks blood flow.
Heart muscle cells are unusually intolerant of low oxygen, they can only survive a few minutes without it. So once the blockage happens, the clock starts ticking almost immediately. This event is what most people call a heart attack, also known as myocardial infarction.
How a Clot Actually Forms, Step by Step
This is where most explanations stop too early. Here’s what’s really happening:
1. Plaque builds up slowly, over years. Cholesterol and fat collect inside your artery walls, forming a plaque. Over time, your immune system sends in cells to “clean up” the area, but this actually makes the plaque grow a soft, fatty core underneath a thin covering.
2. The covering weakens and cracks. Here’s the counterintuitive part: it’s usually not the biggest, most severe-looking plaques that rupture. Smaller plaques with a thin covering are more dangerous, because that thin layer is more likely to tear under normal blood pressure and flow. This is exactly why someone can pass a stress test one month and have a heart attack the next — the scan measures how much the artery is narrowed, not how likely a plaque is to crack open.
3. Your blood reacts like it’s healing a cut. When the plaque cracks, it exposes material underneath that your blood recognizes as “damage.” Sticky blood cells called platelets rush to the site and clump together. At the same time, a chain reaction of clotting proteins in your blood gets triggered, ending in the production of a mesh-like protein called fibrin, which reinforces the clot and holds it in place.
4. The clot grows and can block the artery. Depending on how much clotting material is exposed and how your body’s clot-dissolving system responds, the clot either stays small and gets sealed over, until it fully blocks blood flow.
Which Artery Matters — Because Symptoms Differ
Not all coronary thrombosis events look the same, because different arteries feed different parts of the heart:
- Front of the heart (fed by the left anterior descending artery): This is the largest territory, so a blockage here tends to be the most dangerous. It’s sometimes nicknamed the “widow-maker” artery for that reason.
- Bottom of the heart (fed by the right coronary artery): Blockages here are more likely to cause slow or irregular heartbeats, because this artery also usually feeds the heart’s natural electrical “pacemaker” tissue.
- Side of the heart (fed by the left circumflex artery): Blockages here can be sneakier to diagnose because they sometimes don’t show up as clearly on a standard heart tracing.
This is part of why two people having a heart attack can have completely different symptoms and warning signs, it genuinely depends on which artery is involved.
Warning Signs to Know
- Chest pain, tightness, or pressure — often described as squeezing
- Pain spreading to the arm, jaw, neck, and back
- Shortness of breath
- Cold sweat, nausea, and feeling lightheaded
Important for women: classic chest pain isn’t always the main symptom. Fatigue, indigestion-like discomfort, and breathlessness are common, and sometimes the only signs — which is a big reason heart attacks in women get diagnosed too late.
Two Types of Heart Attack, and Why the Difference Matters
Doctors split heart attacks caused by coronary thrombosis into two categories, and this isn’t just medical paperwork, it changes how fast you’re treated:
- A “complete blockage” heart attack (STEMI). The artery is fully blocked, and it shows up immediately on a heart tracing (ECG) as a specific pattern. This is treated as the most extreme emergency, hospitals aim to reopen the artery within 90 minutes of a patient walking through the door.
- A “partial blockage” heart attack (NSTEMI). The artery is narrowed but not fully closed, or the clot is opening and closing on its own. This doesn’t always show up clearly on the ECG right away, so doctors rely more heavily on blood tests to confirm it, and treatment timing is usually within a day or two rather than immediate.
Who’s Most at Risk?
- High cholesterol (specifically LDL, the “bad” kind) — this is the raw material plaques are built from
- High blood pressure — the constant extra force makes plaques more likely to crack
- Smoking — makes your blood more prone to clotting and damages the artery lining
- Diabetes or insulin resistance — high blood sugar makes plaque coverings weaker and slower to heal
- Being overweight or inactive
- A family history of early heart disease
- Age — risk increases after 45 for men and 55 for women
How Coronary Thrombosis Is Diagnosed
If you show up at the hospital with heart attack symptoms, here’s the typical order of events:
- ECG first. A quick, painless test that reads your heart’s electrical activity through pads on your chest. It’s usually the very first thing done, and it can immediately reveal a complete blockage.
- Blood tests. Doctors check for a protein called troponin, which leaks into your blood when heart muscle is damaged. It becomes detectable within a few hours of the injury and stays elevated for over a week, making it a reliable way to confirm a heart attack even days later.
- Coronary angiography. This is the test that pinpoints exactly where the blockage is. A thin, flexible tube is guided through a blood vessel, usually from the wrist up into the coronary arteries, and a contrast dye is injected so the blockage shows up clearly on a live X-ray. If a blockage is found, doctors can open it in that same procedure.
- Special imaging in tricky cases. Occasionally, symptoms and initial scans don’t line up cleanly, someone might have all the signs of a heart attack, but the angiogram doesn’t show an obvious blockage. In these cases, doctors can use miniature ultrasound probes threaded directly into the artery to look for a clot that’s otherwise hard to see.
What Are the Chances of Recovery?
Coronary thrombosis is genuinely serious, it’s responsible for around a third of sudden cardiac deaths in the U.S. Older studies going back decades found that roughly 1 in 3 people didn’t survive the initial event, and among survivors, a meaningful number still faced a difficult first year afterward.
The encouraging news: outcomes today are dramatically better than those older numbers suggest. Two things changed this — getting patients to treatment much faster, and better long-term medications afterward, particularly blood thinners and cholesterol-lowering drugs. Today, how someone recovers mostly comes down to how much heart muscle was damaged and how quickly they got treated.
How It’s Treated
- Clot-dissolving drugs, given in some cases to chemically break up the clot when a hospital with a cath lab isn’t immediately reachable
- Angioplasty and stents — a small balloon is inflated inside the blocked artery to reopen it, and a mesh tube called a stent is usually left in place to hold it open long-term
- Bypass surgery, for more widespread blockages that aren’t well suited to a stent
- Blood-thinning medications, like aspirin and other platelet-blocking drugs, which reduce the chance of a new clot forming, often prescribed together and taken for months afterward
What Recovery Really Looks Like
Surviving the event is just step one. What happens in the months after matters just as much:
- Cardiac rehab. A supervised program of gradually increasing exercise, education, and support. People who complete it consistently do better long-term, it’s a proven part of treatment, not an optional add-on.
- Taking your medications, consistently. Stopping cholesterol medication too early is one of the most common, and most preventable, reasons people end up back in the hospital with a second clot.
- Fixing the root causes. Lowering cholesterol, quitting smoking, and managing blood sugar aren’t just general wellness advice here, each one directly interferes with the exact process that caused the first clot to form.
- Regular checkups. Your doctor will track how well your heart is pumping and watch closely for new symptoms, especially during the first year, when the risk of another event is highest.
Recovery isn’t a finish line, it’s something you actively maintain.
The Bottom Line
Coronary thrombosis is what happens when years of quiet, invisible damage inside your arteries suddenly turns into an emergency. It’s not a random event, it follows a specific chain reaction, from a weak spot in a plaque, to a clot, to a blocked artery.
The good news is that nearly every step in that chain is something you can influence: the risk factors driving it are almost all manageable, and the earlier you act on them, the less likely you are to experience this moment yourself.