Coronary Thrombosis vs Ischemic Stroke: How Are They Different?
Coronary Thrombosis vs Ischemic Stroke: Why They’re Not the Same Thing
Table of Contents
You’ve probably heard that a heart attack and a stroke can both come from a blood clot. So it’s natural to assume the clot behaves the same way in both cases. It doesn’t.
The clot that causes a heart attack and the clot that causes a stroke often have completely different backstories. The difference isn’t just “one hits the heart, the other hits the brain.” It comes down to something more basic: where the clot actually forms, what sets it off, whether it stays put in the body before it causes trouble.
This isn’t guesswork. It’s backed by decades of autopsy research and major clinical studies.
In one popular autopsy study, researchers looked at 113 men with coronary artery disease who died suddenly. They found active clots in 59 of them. Of those 59, 41 were linked to a ruptured plaque and 18 were linked to plaque erosion, a milder kind of surface damage. That tells us something important: coronary clots usually form right on top of a damaged patch inside the artery wall. This comes from Burke and colleagues’ landmark study in the New England Journal of Medicine.
Stroke is a messier picture. The famous TOAST study, which is still the standard way doctors classify strokes, found that ischemic strokes can come from several different causes, including a clot that traveled from the heart.
In other words, a stroke clot might form right where it causes damage, and drift into the brain. The original TOAST study is what made this distinction the backbone of modern stroke diagnosis. That’s the real story behind coronary thrombosis vs ischemic stroke, and it’s more interesting than most articles let on.
Location Is Everything
Here’s the easiest way to think about it:
With a coronary thrombosis, the clot usually builds right on top of a diseased patch inside the coronary artery, and it grows exactly where it ends up causing the blockage. With an ischemic stroke, the clot might form locally too, but it can also form somewhere else, ride through the bloodstream, and get stuck in a brain artery far from where it started.
So really, you’re looking at two different clot stories:
Coronary Thrombosis: Damage to the artery wall leads to a clot forming right there, and that clot keeps growing until it chokes off blood flow in that exact spot.
Cardioembolic Stroke: A clot forms inside the heart, a piece breaks off, it travels through the bloodstream, and it eventually gets wedged in a brain artery.
That one difference, forming locally versus arriving from somewhere else, changes everything about how doctors track down the cause of the blockage.
What Actually Happens During Coronary Thrombosis
Coronary thrombosis is when a blood clot forms inside one of the coronary arteries, the vessels that feed oxygen rich blood to your heart muscle.
If that clot grows big enough to seriously choke off blood flow, the heart tissue downstream starts starving for oxygen.
If the blockage lasts too long, that starved tissue can die. That’s a heart attack.
But how does the clot actually get there in the first place? Autopsy studies on people who died from sudden cardiac events gave researchers a direct look.
What Doctors Found When They Looked Inside Damaged Coronary Arteries
One of the most important studies here was done by Davies and Thomas, published in 1984 in the New England Journal of Medicine.
They examined 100 people who died from ischemic heart disease within six hours of their symptoms starting. They found active clots inside the coronary arteries in 74 of them. Even among the 26 who didn’t have a clot blocking the vessel, 21 still showed cracking in their arterial plaque. The researchers concluded that sudden cardiac death usually involves a coronary lesion that changes fast, with the plaque cracking open and a clot forming right after. You can read the original paper, “Thrombosis and Acute Coronary-Artery Lesions in Sudden Cardiac Ischemic Death,” if you want the full data.
This finding matters because it kills a common myth: that a coronary artery just slowly clogs up like a drainpipe filling with sludge over years.
That’s not usually what happens.
Something sudden happens first. A plaque inside the artery cracks or wears down. Then the body’s clotting system kicks in almost immediately.
Step 1: A Damaged Plaque Starts the Whole Chain Reaction
Atherosclerosis is the slow buildup of fatty plaque inside your artery walls, something most people are somewhat familiar with. But here’s what a lot of people don’t know: the plaques most likely to trigger a heart attack aren’t necessarily the ones that make the artery the narrowest. It’s the unstable ones, the plaques prone to rupturing or eroding, that cause the real danger.
When a plaque ruptures, its protective outer cap tears open. That exposes the blood to material underneath that’s extremely good at triggering clots.
Your body reacts almost instantly. Platelets rush to the injury site, stick to it, activate, and call in more platelets. At the same time, your clotting system produces fibrin, a protein that acts like a net, holding the whole clot together.
This isn’t theory. It’s exactly what Burke’s 1997 study documented directly. Among the 59 men with active coronary clots, two patterns showed up:
- 41 clots were linked to a ruptured plaque
- 18 clots were linked to plaque erosion, meaning the surface simply wore away rather than tearing
So coronary thrombosis doesn’t happen the exact same way in every single case, but in both patterns the clot forms right at the site of damage inside the artery wall. Read the full Burke et al. study here.
How a Heart Attack Clot Actually Behaves
This is where things get interesting when you compare it to a stroke clot.
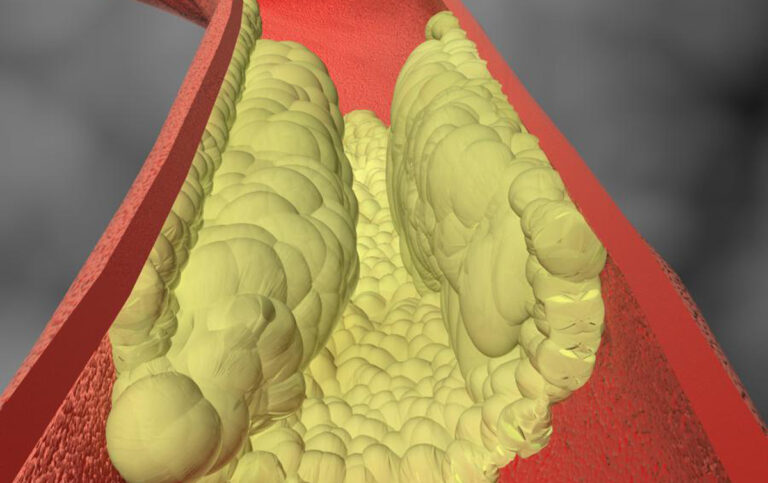
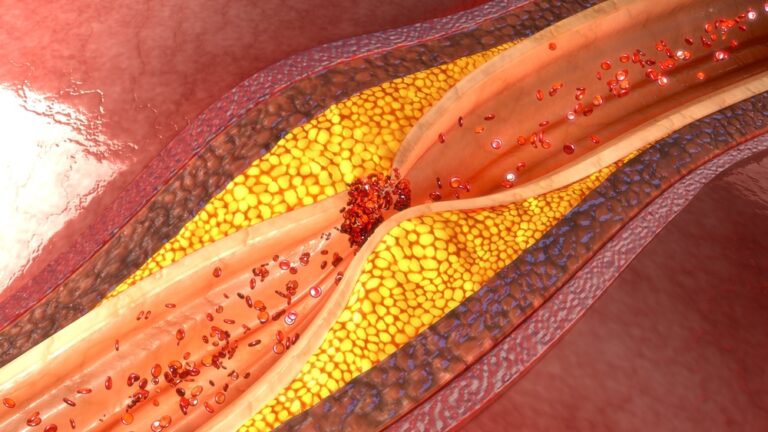
Picture the coronary artery as a narrow tunnel, and picture the atherosclerotic plaque as a bump sticking out from one wall of that tunnel.
When that bump ruptures or erodes, the clot doesn’t usually start off as some free floating chunk drifting through your bloodstream. It starts right there, at the site of the injury.
From there, the clot grows outward into the lumen, which is just the open channel through which your blood actually flows.
Here’s the typical sequence:
Coronary plaque develops over time
↓
The plaque ruptures or erodes
↓
Platelets stick to the damaged surface
↓
Fibrin locks the clot together
↓
The clot expands into the open channel of the artery
↓
Blood flow gets restricted more and more
↓
Heart muscle downstream starts running low on oxygen
So a typical heart attack clot behaves less like a traveler moving through your body and more like something that grows right at the scene of the injury.
That doesn’t mean it happens slowly. The Davies and Thomas research showed the opposite can be true, that the coronary lesion can change extremely fast. That’s why someone can feel completely fine one moment and be in the middle of a heart attack the next, even though the underlying artery disease had been quietly building for years. Their study found active clots and coronary damage in people who died within hours of their symptoms starting.
Here’s the key takeaway worth remembering:
Plaque disease can sit there quietly for years, but once it cracks open, the resulting clot can become a fast moving, dangerous event within minutes to hours.
What Actually Happens During an Ischemic Stroke
An ischemic stroke happens when blood flow to part of the brain gets cut off, usually because something is physically blocking an artery. That something is a blood clot. But here’s where a lot of health articles get sloppy: they talk about “the stroke clot” as if there’s only one kind. There isn’t.
The TOAST study, short for Trial of Org 10172 in Acute Stroke Treatment, sorted ischemic strokes into 5 major categories based on their cause:
- Disease in a large artery (large-artery atherosclerosis)
- A clot that traveled from the heart (cardioembolism)
- Blockage in a small, deep blood vessel (small-vessel occlusion)
- Stroke from another identified cause
- Stroke where the cause couldn’t be determined
The single biggest lesson from this study is this: an ischemic stroke is not one single type of clotting event.
Some strokes happen because a clot builds locally, right at the site of arterial damage. Others happen because material from somewhere else in the body breaks loose and travels to the brain. See the original TOAST classification study.
That makes stroke a much more varied condition than a heart attack when it comes to how the clot actually behaves.
Thrombotic Stroke: When the Clot Builds Right Where It Blocks
A thrombotic ischemic stroke is the type that behaves most like a classic heart attack clot.
In this case, existing disease inside an artery encourages a clot to form right at, or very close to, the exact spot where the blockage ends up happening.
For example, atherosclerosis affecting a large artery in the neck or brain can trigger a clot to grow locally, the same basic process as in the heart.
The sequence looks conceptually similar to coronary thrombosis:
Existing arterial disease
↓
The vessel surface gets damaged
↓
Clotting activates right at that spot
↓
The clot forms and keeps growing
↓
Blood flow to the tissue downstream drops or stops completely
The difference here isn’t the biology of how a clot forms. It’s what tissue ends up starved of blood.
With a heart attack, it’s heart muscle. With a thrombotic stroke, it’s brain tissue.
So it would actually be wrong to say “heart clots stay put while stroke clots always travel.” The TOAST research itself proves that’s an oversimplification, since large-artery disease and clots that traveled from the heart are two separate stroke categories. The study clearly separates these stroke subtypes.
Embolic Stroke: When the Clot Travels Before It Causes Damage
Now here’s the type of stroke that looks nothing like a typical heart attack clot.
In an embolic ischemic stroke, the clot, doesn’t necessarily form in the brain artery where it ends up getting stuck. It forms somewhere else in the body first.
One source is the heart itself. A clot forms inside a heart chamber. A piece of it breaks off. That piece, now called an embolus, enters the bloodstream and travels along with normal blood flow until it hits an artery too narrow to pass through. That’s where it gets lodged.
Here’s the typical sequence:
A clot forms inside the heart
↓
Part of the clot breaks free
↓
The loose piece enters general circulation
↓
It travels toward the brain
↓
It reaches a brain artery too narrow to pass
↓
It gets stuck there
↓
Blood flow to that part of the brain is cut off
This is a completely different spatial pattern compared to a coronary plaque rupture.
With a heart attack, doctors usually find the damaged plaque and the clot in the exact same location. With a stroke caused by a traveling clot from the heart, doctors find the blockage in the brain, but they then have to hunt elsewhere in the body, often in the heart itself, to figure out where the original clot actually came from.
That’s why the TOAST classification isn’t just a label. It answers a clinical question that changes treatment:
Did the clot form right where the blockage happened, or did it travel there from somewhere else?
Coronary Thrombosis vs Ischemic Stroke: A Side by Side Comparison
| Question | Heart Attack Clot (Coronary Thrombosis) | Stroke Clot (Ischemic Stroke) |
|---|---|---|
| Where does it usually form? | Right on the diseased coronary plaque | Either locally in an artery, or somewhere else entirely |
| What usually triggers it? | Plaque rupture or plaque erosion | Depends heavily on which stroke type it is |
| Does it stay where it started? | Yes, in the classic pattern, the clot builds right at the culprit lesion | Not always. Traveling clots are common, especially in strokes caused by the heart |
| Can the origin and the blockage be in different places? | Rare in typical plaque related heart attacks | Yes, especially with cardioembolic stroke |
| What artery does it block? | A coronary artery feeding the heart | An artery feeding the brain |
| What’s the downstream effect? | Heart muscle starved of oxygen, possible heart attack | Brain tissue starved of oxygen, possible stroke damage |
The biggest lesson from this table: the difference usually isn’t what the clot is made of. It’s where the clot came from and how it got to the artery it eventually blocked.
Why “Heart Clots Stay, Stroke Clots Travel” Is Too Simple
You’ll often see this claim floating around online:
“Heart clots stay where they form, stroke clots travel.”
That’s a nice, tidy sentence. It’s also not fully accurate.
Some stroke clots form locally, just like heart attack clots.
The TOAST classification includes large-artery atherosclerosis, a category where the clot doesn’t need to travel from the heart at all. The original classification makes it clear that ischemic stroke has multiple distinct causes.
Some stroke clots absolutely do travel.
Cardioembolism is a major, well documented stroke category. The clot’s origin is the heart, but the damage happens in the brain.
Even coronary thrombosis isn’t one single mechanism.
The Burke study showed heart attack clots can come from either plaque rupture or plaque erosion, two different processes. Of the 59 active coronary clots in that study, 41 involved rupture and 18 involved erosion.
So the honest, evidence backed conclusion looks more like this:
A typical heart attack clot is usually a locally triggered event, building right on a damaged coronary plaque. An ischemic stroke, on the other hand, covers several different mechanisms, some local, some involving clots that traveled a long way from where they started.
What These Landmark Studies Teach Us About Heart Attacks
The reason the Davies, Thomas, and Burke studies matter so much is that they looked at the actual physical anatomy of acute coronary events in real people, not just theory.
Davies and Thomas found active clots in 74 out of 100 people who died from ischemic heart disease within six hours of their symptoms starting. Even most of the remaining 26 without a full blocking clot still had cracked plaque. Their conclusion was that sudden cardiac death typically involves a coronary lesion that changes rapidly, with plaque damage and clot formation happening together. Read the study’s findings here.
Then Burke’s 1997 study examined 113 men with coronary disease who died suddenly, and found active clots tied to both plaque rupture and plaque erosion. The full NEJM study lays out direct evidence for both of these pathways.
Together, these two studies support a powerful idea: coronary thrombosis is often the body’s reaction to a sudden, local breakdown inside the artery wall.
The plaque has usually been quietly building for years.
But then something changes right at the surface of that plaque.
The artery wall suddenly becomes primed for clotting.
The clot forms right there.
And that clot can become the exact event that turns years of silent artery disease into a full blown, acute heart emergency.
Why an Embolic Stroke Is Different: The Brain Isn’t Always the Source of the Problem
With an embolic stroke, the brain artery where the clot gets stuck isn’t where the real problem started. That’s one of the most clinically important differences between an embolic stroke and a classic heart attack clot.
A brain scan might clearly show a blocked artery. But finding that blockage doesn’t automatically answer the bigger question: where did that clot actually come from?
Doctors have to look beyond the brain entirely, checking the heart and other parts of the circulatory system to track down the true source. This is exactly why the TOAST classification exists. Figuring out the stroke subtype genuinely changes how doctors evaluate the patient, what treatment they choose, and what the long term outlook looks like. The TOAST investigators specifically pointed out that stroke cause directly affects prognosis and management.
That’s why an embolic stroke can really be thought of as a two location story:
- Location one: where the clot actually started.
- Location two: where it finally got stuck and caused the damage.
A classic heart attack clot, by comparison, is usually a one location story. The diseased plaque triggers the clot, and that same spot is where the blockage ends up happening.
A Quick Visual Recap
Coronary Thrombosis
A diseased coronary plaque exists
↓
The plaque ruptures or erodes
↓
Platelets and clotting factors activate right there
↓
A clot forms directly on the damaged lesion
↓
The clot grows into the open channel of the artery
↓
Blood flow to the heart drops or stops
↓
Heart muscle becomes starved of oxygen
Stroke Clot That Traveled From the Heart (Cardioembolic Stroke)
A clot forms inside the heart
↓
Part of that clot breaks off
↓
The loose piece travels through the bloodstream
↓
It reaches the arteries feeding the brain
↓
It hits a vessel too narrow to pass through
↓
It becomes lodged there
↓
Brain tissue downstream is starved of oxygen
This is why the two conditions can look strikingly similar at the finish line, a blocked artery and oxygen starved tissue, while having completely different origin stories.
Does Every Coronary Clot Cause a Heart Attack?
Not necessarily.
Whether a coronary clot actually leads to a heart attack depends on several factors:
- How much of the artery is actually blocked
- How long the blockage lasts
- Which specific coronary artery is affected
- How much heart muscle depends on blood flow from that artery
- Whether the heart has any backup blood supply available
A clot can partially reduce blood flow without completely and permanently blocking the artery. But if the blockage is severe enough and lasts long enough, the heart muscle downstream can suffer permanent, irreversible damage, and that’s when a myocardial infarction occurs.
Here’s the key point worth remembering from this entire comparison: a clot’s behavior is not fixed. It’s dynamic.
It can keep growing.
It can change how much it’s actually blocking. And the clinical picture can get more serious the more blood flow drops.
The Davies and Thomas research is especially useful here because it shows that acute coronary lesions can change fast, rather than representing some simple, static blockage that just sits there unchanged. Their findings support the idea of an actively evolving coronary lesion with ongoing clot formation.
The bottom line: a heart attack clot and a stroke clot can both start from a damaged artery wall, but they don’t always play by the same rules. One usually stays and grows right where the damage began. The other might travel across your entire circulatory system before it ever causes harm. Knowing which pattern you’re dealing with is exactly why doctors don’t treat every clot the same way, and it’s why understanding your own risk factors, whether that’s heart disease, atrial fibrillation, or artery disease elsewhere in your body, matters more than most people realize.