Coronary Sinus Thrombosis: Causes, Symptoms, and Treatment Explained
Coronary Sinus Thrombosis: The Rare Heart Vein Clot That Can Mimic a Heart Attack
Table of Contents
Most people who hear the word “thrombosis” near the heart automatically think of a heart attack. A clogged artery. A sudden collapse.
But there is a second, far rarer type of heart clot that most people, and even some doctors, have never heard of. It does not form in an artery. It forms in a vein deep inside the heart called the coronary sinus.
This condition is called coronary sinus thrombosis, CST for short.
CST is so uncommon that most of what doctors know about it comes from single patient case reports rather than large studies involving thousands of people.
A 2025 review that combed through medical literature published between 1974 and December 2024 found something interesting. CST does not behave the same way in every patient.
In some people it grows slowly and barely causes any trouble. In others it develops suddenly and becomes a life threatening emergency within hours.
That is what makes CST such a tricky condition to understand, and why this article breaks it down: what it is, what causes it, what symptoms actually show up in real patients, how doctors find it, and what the evidence says about treating it.
Quick disclaimer: This article explains coronary sinus thrombosis based on published medical research. It is written to help you understand the condition. It is not meant to diagnose or treat anyone. If you have symptoms, see a doctor.
What Exactly Is the Coronary Sinus?
Before you can understand coronary sinus thrombosis, you need a quick picture of how blood moves through the heart muscle itself.
Your coronary arteries deliver fresh, oxygen-rich blood to the heart muscle. That part most people already know.
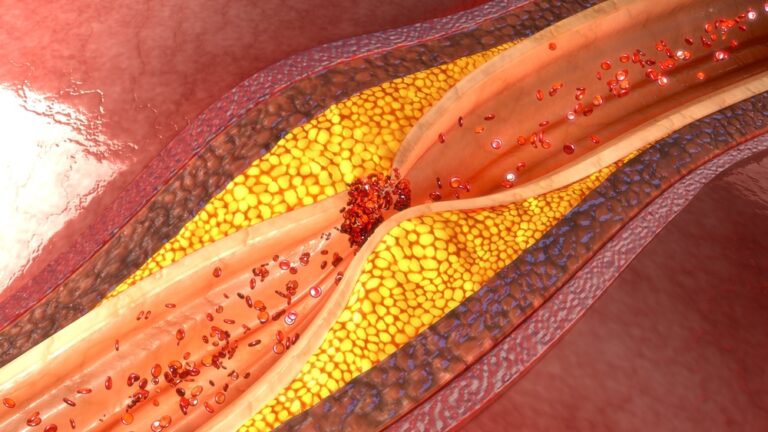
But once the heart muscle uses up that oxygen, the blood has to leave. It doesn’t disappear. It drains through a network of small cardiac veins that all feed into one larger collecting vessel called coronary sinus. From there, blood empties directly into the right atrium, one of the heart’s upper chambers.
Think of it this way:
Heart muscle sends used blood → into small cardiac veins → into the coronary sinus → into the right atrium
The coronary sinus is basically the heart’s main drainage pipe for its own tissue.
When a blood clot forms inside that pipe and blocks it, that is coronary sinus thrombosis.
This is a completely different problem from a regular heart attack. A heart attack happens when a clot blocks an artery and stops blood from reaching the heart muscle. CST happens when a clot blocks the vein that carries blood away from the heart muscle. One is a supply problem. The other is a drainage problem.
The 2025 review describes the coronary sinus as the main collection point for cardiac venous blood, receiving drainage from several major cardiac veins before it empties into the right atrium.
Why Does a Clot in a Heart Vein Actually Matter?
It is easy to assume that a clogged vein is less dangerous than a clogged artery. That assumption can be wrong.
The heart muscle needs good drainage just as much as it needs good blood supply. If the coronary sinus becomes blocked, blood pressure inside the small cardiac veins upstream of the blockage can start to rise. Over time, that backup can interfere with how well the heart muscle functions.
Here is the part that makes CST unpredictable. The coronary venous system is not a single, one way pipe. It has multiple connections and backup routes, called collateral pathways, that can sometimes carry blood around a blockage.
This is likely why some people with CST barely notice anything wrong, while others develop a sudden, dangerous drop in heart function. The 2025 review makes this same point, separating CST cases into two broad groups: fast moving acute cases and slower, partial cases that may go unnoticed for longer.
What Causes Coronary Sinus Thrombosis?
There is no single cause of CST. Instead, doctors have identified several different situations where it tends to show up.
1. Heart Procedures That Involve Wires, Catheters, or Devices
The clearest pattern in the medical literature connects CST to procedures where doctors insert catheters, into the right side of the heart.
This includes:
- Catheter based heart procedures
- Electrophysiology procedures, which are used to fix abnormal heart rhythms
- Pacemaker implantation
- Central line placement through a large vein near the heart
- Any other instrumentation that touches the coronary sinus
The reasoning is straightforward. When a catheter rubs against the inner lining of a blood vessel, it can injure that lining.
Damaged vessel walls are one of the three classic triggers for clot formation, a concept doctors call Virchow’s triad.
A 2010 case report shows exactly how serious this can get. An 11 year old boy underwent an ablation procedure to fix a fast heart rhythm called supraventricular tachycardia. Shortly afterward, he developed a coronary sinus clot. His chest pain got worse, his ECG showed ST segment elevation, fluid built up around his heart, and he went into cardiogenic shock, meaning his heart could no longer pump enough blood to keep his body stable. Doctors rushed him into the cath lab and used a suction based device to physically remove the clot. He recovered dramatically.
That case tells us something important: CST is not always a mystery illness. Sometimes it is a direct, traceable complication of a heart procedure.
2. Blood That Moves Too Slowly Through the Coronary Sinus
Sometimes the problem has nothing to do with an injury at all. It has to do with how fast, or how slowly, blood moves.
When blood flow slows down in one spot, clotting risk goes up. This is true anywhere in the body, not just the heart.
A 2024 case published in JACC Case Reports describes a 62 year old man whose coronary sinus was enormous, far bigger than normal, and packed with clots. The doctors believed that blood was essentially pooling and stagnating inside this oversized vessel, creating the perfect environment for a clot to form. They also checked for other explanations, including cancer and abnormal vein connections, before settling on stagnant flow as the likely cause.
This case teaches an important lesson. The coronary sinus does not have to be physically damaged for a clot to form there. Sometimes the shape and size of the vessel itself, combined with sluggish blood flow, is enough.
3. Unusual Vein Anatomy People Are Born With
Some people are simply born with coronary vein anatomy that is different from the typical layout.
The 2025 review points to a specific condition called persistent left superior vena cava. Normally, a vein on the left side of the chest that exists early in fetal development disappears before birth. In some people it never disappears, and instead drains directly into the coronary sinus, changing how blood flows through it.
Another anatomical variation is called an unroofed coronary sinus, where part of the wall separating the coronary sinus from a heart chamber is missing.
The 2024 JACC case notes that an enlarged coronary sinus can also show up in people with high pressure on the right side of the heart, such as those with pulmonary hypertension.
These anatomical quirks matter because they change how smoothly, blood flows through the vessel.
4. Medical Conditions That Make Blood Clot More Easily
Certain health conditions raise a person’s risk of forming blood clots anywhere in the body, including the coronary sinus. These include:
- Cancer
- Active infection
- Inflammatory diseases
- Inherited clotting disorders
- Certain other heart conditions
It is worth being careful here. Because CST is so rare, most of what links it to these conditions comes from individual patient stories rather than large scale proof that any one condition directly causes CST.
5. Sometimes Doctors Never Find a Clear Cause
This category is called idiopathic CST, meaning doctors investigate thoroughly and still cannot pinpoint a definite trigger.
The 2024 JACC case is a good real world example. After ruling out cancer and other structural problems, the doctors concluded the most likely explanation was simply stagnant blood flow inside an unusually large coronary sinus. They started the patient on long term blood thinners and followed him for three years with no complications.
What Symptoms Does Coronary Sinus Thrombosis Actually Cause?
Here is one of the most frustrating things about CST. It does not have one clear, recognizable symptom pattern.
How a patient feels depends on three things: how fast the clot formed, how completely it is blocking the vessel, and whether the body’s backup drainage routes can compensate.
Chest Pain
Chest pain shows up in many acute CST cases.
In the 2010 case, the young patient’s chest pain appeared alongside ST segment elevation on his ECG, a warning sign doctors normally associate with a classic heart attack, and he later became hemodynamically unstable, meaning his blood pressure and circulation became dangerously unreliable.
But here is the catch. Chest pain by itself tells you almost nothing specific. It shows up in heart attacks, pericarditis, lung problems, and dozens of other conditions that are far more common than CST.
Shortness of Breath
Some patients with CST experience breathlessness, especially when the clot is affecting how well the heart is functioning overall.
This symptom is not unique to CST either. It is simply a sign that something is putting strain on the cardiovascular system.
Irregular Heartbeat
Abnormal heart rhythms have also been reported in CST patients. Again, this symptom overlaps heavily with many other unrelated heart problems.
Severe, Rapid Deterioration
The scariest presentations involve sudden, severe blockage.
The 2010 case is the clearest illustration. What started as chest pain and ST elevation progressed into fluid buildup around the heart and full cardiogenic shock, a true medical emergency.
The 2025 review confirms that acute CST can move fast and turn dangerous quickly.
Some Patients Barely Feel Anything
This is the part most generic health articles leave out entirely.
Not every coronary sinus clot causes a dramatic emergency. When the body’s backup venous routes can carry blood around the blockage, symptoms can be mild or almost unnoticeable.
The 2024 JACC case is a perfect example. The patient had a giant, clot filled coronary sinus, yet the discovery came through routine cardiac imaging rather than through a dramatic collapse.
How Do Doctors Actually Diagnose Coronary Sinus Thrombosis?
There is no blood test that can confirm CST on its own. Diagnosis depends almost entirely on imaging, meaning doctors have to actually see the clot.
Echocardiography (Heart Ultrasound)
An echocardiogram can sometimes catch a mass sitting inside an enlarged coronary sinus.
A 2023 case report shows this in action. A previously healthy 38 year old man came to the emergency room with chest pain. A bedside cardiac ultrasound, the kind performed quickly right in the ER, picked up a coronary sinus thrombosis that nobody was specifically looking for. The doctors pointed out that this type of quick bedside ultrasound can catch CST even outside of a specialized cardiology setting. This matters because it shows echocardiography is not only useful for checking how well the heart is pumping. It can also stumble onto an unusual venous problem that would otherwise be missed.
Cardiac CT Scan
A CT scan can map out the coronary sinus in detail, including:
- The exact size and location of the clot
- The layout of the coronary veins
- Any structural abnormalities nearby
- Other possible explanations for a mass in that area, such as a tumor
The 2025 review lists CT as one of the key imaging tools used to evaluate CST.
Cardiac MRI
MRI can add more detail about the heart’s structure and the tissue makeup of a mass, which is especially helpful when doctors are not yet sure whether they are looking at a clot or something else entirely.
Venography
This is a more invasive test where doctors inject contrast dye directly into the venous system to see blockages or abnormal drainage patterns in real time. Because it is invasive, doctors reserve it for specific situations rather than using it as a first step.
Why Doctors Often Combine Several Imaging Tests
One of the biggest lessons from recent case reports is that a single scan is not always enough.
In the 2024 idiopathic CST case, doctors used both echocardiography and a PET-CT scan together to properly characterize the mass and rule out other explanations, including cancer and abnormal vein drainage. This combined approach matters because a mass sitting inside the coronary sinus is not automatically a blood clot. It could be a tumor, and doctors need enough imaging evidence to tell the difference confidently.
How Is Coronary Sinus Thrombosis Treated?
This is where separating solid evidence from guesswork becomes especially important.
There are no large randomized trials that establish one official treatment protocol for CST. Because the condition is so rare, treatment decisions are based mostly on published case reports and expert judgment, not massive clinical studies.
The 2025 comprehensive review identifies blood thinners, known medically as anticoagulation, as the main treatment approach, with surgical clot removal reserved for the most severe or stubborn cases.
Blood Thinners
Anticoagulant drugs work by preventing the clot from growing larger while giving the body’s own clot dissolving system time to work.
The specific drug, dose, and how long a patient needs to stay on it depends entirely on that individual patient’s situation and must be decided by their treating doctor.
The 2024 JACC case offers a real world example. Because the doctors believed stagnant blood flow inside the giant coronary sinus was the main driver, they put the patient on lifelong blood thinners. Three years later, he had no complications.
That does not mean every CST patient needs blood thinners for life. It simply shows how treatment gets tailored to each patient’s specific anatomy and risk of the clot coming back.
Treating Whatever Caused It
Blood thinners alone do not fix the reason the clot formed in the first place.
If CST is connected to a recent heart procedure, an abnormal vein connection, a clotting disorder, an infection, cancer, doctors typically need to address that root cause as well.
Removing the Clot Directly
In severe cases, doctors may need to physically remove the clot.
The 2010 case is the best example of this. Once the young patient went into cardiogenic shock, doctors performed emergency catheterization and used a suction based thrombectomy device to pull the clot out. He recovered dramatically afterward.
This shows that mechanical clot removal is a real option when a patient’s life is in immediate danger.
The 2025 review also lists surgical thrombectomy as an option for treatment resistant cases.
That said, this is a specialized procedure. It is not something every CST patient needs.
What Happens If Coronary Sinus Thrombosis Goes Untreated?
The outcome really depends on what type of thrombosis a person has.
A small, partial clot that develops slowly can behave very differently from a large clot that forms suddenly and blocks the vessel completely.
When collateral venous pathways are able to reroute blood flow, the consequences of a blockage can stay relatively mild. When the blockage is sudden and extensive, complications can escalate quickly and become dangerous.
This is exactly why catching CST early matters, even though it is rare. The goal is not to assume every case will turn into an emergency. The goal is to recognize how differently this condition can behave from one patient to the next.
Coronary Sinus Thrombosis vs. Coronary Artery Thrombosis: What Is the Difference?
These two conditions sound similar but involve completely opposite sides of the heart’s blood flow system.
| Feature | Coronary sinus thrombosis | Coronary artery thrombosis |
|---|---|---|
| Vessel involved | Coronary sinus | Coronary artery |
| Type of vessel | Vein | Artery |
| Main job of the vessel | Drains blood away from the heart muscle | Delivers blood to the heart muscle |
| The core problem | Blood cannot leave the heart muscle properly | Blood cannot reach the heart muscle |
| How common it is | Extremely rare | Much more common |
| How it is usually found | Cardiac imaging | ECG, blood tests (troponin), coronary imaging |
| General treatment approach | Blood thinners for many cases, intervention for severe cases | Antiplatelet or antithrombotic drugs and procedures to reopen the artery |
This is more than a technical distinction.
Coronary sinus thrombosis is not simply another term for a heart attack.
That said, severe CST can still produce chest pain and abnormal ECG patterns that look a lot like a classic heart attack. The 2010 case, with its ST segment elevation, is a striking example of how confusing this overlap can get for doctors trying to make a fast diagnosis.
Why Is Coronary Sinus Thrombosis So Hard to Recognize?
The published cases reveal a consistent problem. CST does not follow one predictable script.
One patient develops it right after a heart procedure.
Another has an unusually large coronary sinus with sluggish blood flow.
Another was simply born with unusual vein anatomy.
Another shows up with chest pain and an ECG that looks like a textbook heart attack.
And another has it discovered almost by accident during a routine ultrasound.
The 2025 review highlights both this unpredictable presentation and why imaging plays such a central role in catching it.
What the Evidence Actually Tells Us
Pulling these individual cases together, several patterns stand out.
CST can follow a heart procedure. Catheterization, pacing procedures, and electrophysiology work show up repeatedly in the published cases.
CST can also appear with no obvious trigger. The 2023 report describes a case discovered by bedside ultrasound in a patient with no history of heart procedures at all.
Unusual coronary sinus anatomy plays a real role. The 2024 giant coronary sinus case shows how slow, pooling blood flow combined with abnormal vessel size can trigger clotting even without any direct injury.
Symptoms range from almost nothing to life threatening. Some cases are found incidentally. Others involve full cardiogenic shock.
Imaging is the backbone of diagnosis. Echocardiography, CT, MRI, and venography each play a role, and complicated cases often need more than one type of scan.
Treatment has to be personalized. Blood thinners are the primary approach in most published cases, but severe cases may need clot removal. There simply is not enough large scale evidence yet to create one single treatment rule for every patient.
Read also: Coronary Thrombosis Explained: Causes, Warning Signs, and Recovery
Frequently Asked Questions
Is coronary sinus thrombosis common?
No, it is extremely rare. Almost everything doctors know about it comes from individual case reports and small literature reviews rather than large clinical trials. A 2025 review specifically analyzed published cases from 1974 through 2024.
What is the most common cause of coronary sinus thrombosis?
There is no single most common cause. Heart procedures and instrumentation show up frequently in the literature, but slow blood flow, unusual vein anatomy present from birth, cancer, infection, and clotting disorders have all been reported as well.
Can coronary sinus thrombosis happen without any procedure or injury?
Yes. A 2023 case describes spontaneous CST discovered by bedside ultrasound in a previously healthy 38 year old man with no history of heart procedures.
Can coronary sinus thrombosis cause chest pain?
Yes, chest pain has been reported in acute cases. But chest pain alone cannot tell you it is CST, since it is a symptom of many far more common heart and lung conditions.
Can coronary sinus thrombosis cause a heart attack?
Not in the traditional sense. A heart attack involves a blocked artery. CST involves a blocked vein. However, severe CST can produce chest pain and ECG changes that closely resemble a classic heart attack.
How do doctors diagnose coronary sinus thrombosis?
Through imaging. Echocardiography, cardiac CT, MRI, and venography are the main tools, and doctors sometimes need to combine more than one to confirm the diagnosis.
Can a regular echocardiogram catch coronary sinus thrombosis?
Yes. Published cases show that both standard and bedside point of care echocardiography have successfully identified clots inside an enlarged coronary sinus.
Is coronary sinus thrombosis dangerous?
It depends on the case. Some patients have mild or slowly developing clots that cause few problems. Others develop sudden, extensive blockages that can become life threatening.
What is the treatment for coronary sinus thrombosis?
Blood thinners are the main treatment reported in the literature. Severe cases sometimes require thrombectomy, a procedure to physically remove the clot, or treatment of whatever condition caused it.
Can coronary sinus thrombosis come back after treatment?
It is possible, especially if the original risk factor is still present. The 2025 review stresses the importance of follow up care to watch for recurrence and complications.
The Bottom Line
Coronary sinus thrombosis is one of the rarest forms of heart related blood clots, but the published research offers some genuinely useful takeaways.
It is not simply a “blood clot in the heart” in the way most people picture that phrase.
It is a clot that blocks the heart’s main venous drainage pathway, and how serious it becomes depends on how completely the vessel is blocked, how fast the clot formed, the patient’s individual vein anatomy, and whether backup drainage routes can pick up the slack.
Based on the current evidence, CST can:
- Develop as a complication after a heart procedure
- Appear spontaneously with no clear trigger
- Be connected to unusual coronary vein anatomy present from birth
- Form inside an abnormally large coronary sinus where blood flow has slowed down
- Cause chest pain, shortness of breath, irregular heartbeat, or full cardiovascular collapse
- Sometimes get caught on a routine echocardiogram before any dramatic symptoms appear
- Require more than one imaging test to confirm
- Respond well to blood thinners in many reported cases
- Require emergency clot removal when the blockage is severe or the patient becomes unstable
The honest truth is that the evidence base for CST is still thin. The 2025 comprehensive review is a meaningful step toward pulling scattered case reports into one place, but large scale prospective studies remain difficult simply because so few people ever develop this condition.
That is exactly why doctors have to evaluate each CST case individually, based on the patient’s anatomy and clinical picture, rather than leaning on one universal symptom, test, or treatment plan.
Research Referenced In This Article
- Yi C. Coronary sinus thrombosis: insights from a comprehensive literature review. Thrombosis Journal. 2025. A full review of CST publications from 1974 to 2024 covering presentation, causes, imaging, its link to PLSVC, and treatment.
- Mok CH-F, et al. Idiopathic Coronary Sinus Thrombosis. JACC: Case Reports. 2024. A case of a giant coronary sinus with clots linked to stagnant blood flow.
- Berrin LL, et al. Spontaneous Coronary Sinus Thrombosis Detected by Point-of-care Transthoracic Echo: A Case Report. Clinical Practice and Cases in Emergency Medicine. 2023.
- Yeo KK, et al. Life-threatening coronary sinus thrombosis following catheter ablation: case report and review of literature. Cardiovascular Revascularization Medicine. 2010.
Coronary sinus thrombosis is not a condition you will hear about often, and that is precisely the point. Its rarity, combined with how differently it can show up in different people, is exactly why it deserves clearer, more specific explanations than it usually gets.