Coronary Thrombosis vs Myocardial Infarction: What’s the Difference?
Coronary Thrombosis vs Myocardial Infarction: How to Tell the Differences
Table of Contents
Most people use these two terms like they mean the same thing. They don’t. And the difference really matters, because it changes how doctors diagnose a heart attack, treat it, and predict how the patient will do.
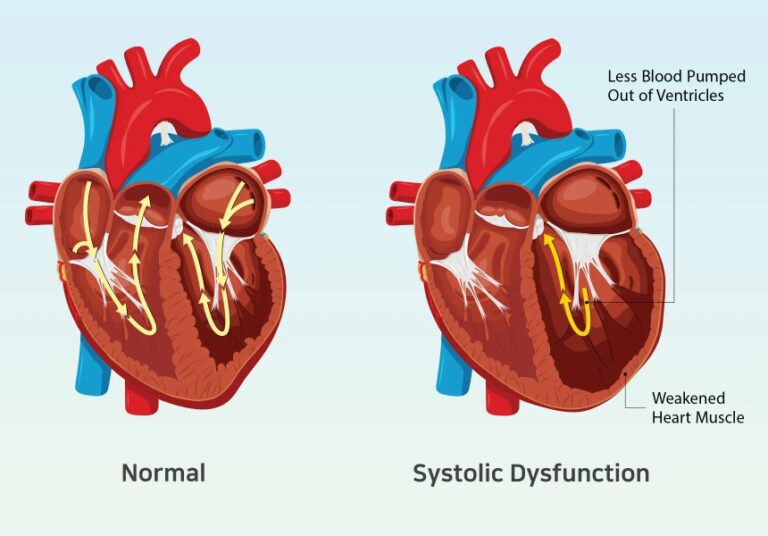
Here’s the simple version. Coronary thrombosis is a blood clot blocking an artery in the heart. It’s a physical event you can see on a scan. Myocardial infarction is heart muscle dying from lack of oxygen.
It’s a diagnosis doctors confirm with blood tests and other evidence. Most of the time, the clot causes the muscle damage. But not always, and those exceptions are exactly what modern cardiology has gotten much better at spotting.
Coronary Thrombosis vs Myocardial Infarction: The Quick Answer
Coronary thrombosis is a clot that forms inside an artery in the heart, usually on top of a patch of plaque that has cracked open or worn away. Myocardial infarction is the heart muscle damage that happens when that blood flow gets cut off for too long. Doctors confirm it by checking a protein in the blood called troponin, along with symptoms and heart test results.
Think of it this way: thrombosis is what you’d see if you looked inside the artery. Infarction is what you’d learn from a blood test and an ECG.
What Coronary Thrombosis Actually Looks Like
A clot doesn’t just form anywhere. Researchers studied 162 people who died from a heart attack and looked closely at their arteries. At the exact spot where the clot had formed, the artery was already severely narrowed, on average about 90 to 91% blocked, even before the clot showed up. Plaque rupture with a clot on top was found to be the cause of more than 90% of heart attacks.
That number surprises a lot of people. Most people picture a heart attack like a pipe slowly clogging until it finally shuts. That’s not quite right. Here’s what actually happens:
A fatty deposit called plaque builds up inside the artery wall over years. It has a soft, fatty center and a thin covering on top. At some point, that covering tears open or wears away. Blood touches the fatty core underneath, and that core is very good at triggering clots. Platelets rush in and stick together, and the whole clotting system kicks into gear. Within minutes, a clot can form right on top of the damaged plaque, turning what used to be a partly narrowed artery into one that’s almost completely blocked.
There are two different ways this damage happens, and it’s worth knowing both because they don’t affect the same people, and they don’t always get treated the same way.
Plaque rupture is the more common cause, behind roughly 75% of sudden heart artery blockages. This is when the thin cap on top of the plaque tears open and exposes the fatty core inside. It’s driven mostly by inflammation, and it shows up more often in men, in smokers, and in people with high cholesterol.
Plaque erosion works differently. The cap on top stays in one piece, but the smooth inner lining of the artery wears away underneath, and a clot forms directly on that rough surface, without any fatty core being exposed. This tends to happen more in younger people and more often in women, and it’s linked more closely to smoking than to cholesterol. One case report described a 23-year-old man who had a heart attack this way. When doctors looked inside his artery with a special imaging tool, they found no plaque buildup or calcium at all, just a clot sitting on an otherwise normal-looking artery wall.
Here’s something else worth knowing: a plaque cracking open doesn’t always mean the artery closes off. Doctors have long known that these small cracks happen fairly often and usually heal quietly on their own, getting absorbed back into the plaque without ever blocking blood flow. So “coronary thrombosis” as a real medical event really means the smaller group of cases where the clot wins the race against the body’s natural clot-control system and blocks the artery long enough to cause damage.
What Doctors Actually Look For to Diagnose a Heart Attack
A lot of health content oversimplifies this. A heart attack isn’t diagnosed just because someone has chest pain and their artery looks bad on a scan. There’s an official, internationally agreed set of rules for diagnosing it, called the Fourth Universal Definition of Myocardial Infarction. Heart associations from the US and Europe put this together jointly.
Under these rules, doctors need to see a rise and fall in a blood protein called troponin, with at least one reading above a set threshold. On top of that, they need at least one of these: symptoms of poor blood flow to the heart, new changes on an ECG, new abnormal patterns called Q waves, imaging showing loss of healthy heart tissue, or a clot actually found on a scan or at autopsy.
Notice something important here: finding a clot is only one of several possible pieces of evidence. It’s not a requirement. A doctor can diagnose a full heart attack using just the troponin blood test and ECG changes, without ever proving a clot exists. That’s the core reason these two terms aren’t the same thing. A heart attack is a diagnosis built from several pieces of evidence together. Coronary thrombosis is just one specific finding.
The official rules also split heart attacks into five types based on what caused them. This is the clearest proof that a clot and a heart attack aren’t the same thing:
- Type 1: Caused by a cracked or worn plaque with a clot on top. This is the classic heart attack, and a clot is central to how it happens.
- Type 2: Caused by the heart simply not getting enough oxygen, with no plaque crack or clot involved at all. Severe anemia, a fast abnormal heart rhythm, low blood pressure, breathing failure, or a dangerous spike in blood pressure can all starve the heart of oxygen even when the artery itself is completely clear.
- Type 3: Sudden cardiac death with symptoms that looked like a heart attack, but there wasn’t time to confirm it with blood tests before the person died.
- Type 4: Happens during or after a procedure to open a blocked artery (like a stent placement).
- Type 5: Happens during or after open heart bypass surgery.
Type 2 is the clearest example that a heart attack doesn’t need a clot at all. The artery can be perfectly healthy, and yet the person still meets every official criteria for having had a heart attack, because their heart muscle is genuinely dying from lack of oxygen.
MINOCA: The Clearest Proof They’re Not the Same Thing
If Type 2 doesn’t convince you, this will. There’s a recognized condition called MINOCA, short for Myocardial Infarction with Non-Obstructive Coronary Arteries. It’s exactly what it sounds like: a real heart attack, confirmed by blood tests, but the arteries on the scan don’t show any major blockage (under 50% narrowing) and there’s no obvious clot to blame.
MINOCA makes up somewhere between 6% and 15% of all heart attacks, depending on the study. It shows up more often in women, and in Black and Latino patients under age 55. And even though the label says “non-obstructive,” meaning no major blockage, people with MINOCA don’t necessarily do better. Their outlook is often just as serious as people with a classic blocked artery.
What actually causes MINOCA? A few different things: plaque damage too small to show up clearly on a standard scan, a sudden spasm in the artery, tiny blood vessel problems too small to see on angiography, a spontaneous tear in the artery wall called SCAD, or a small clot that traveled from somewhere else in the body. In several of these cases, no clot ever forms in the artery itself, yet the heart muscle still gets damaged. This is really the cleanest way to see that a heart attack is defined by what happens to the muscle, not by whether a clot was involved.
How Doctors Tell Rupture From Erosion, and Why It’s Getting Easier
Until fairly recently, doctors mostly guessed at coronary thrombosis rather than actually seeing it. A standard angiogram shows the outline of how blood is flowing through the vessel.
It doesn’t show the plaque or clot sitting inside the artery wall itself, only the shadow that blood flow leaves behind.
That’s changed with newer imaging tools. Optical coherence tomography (OCT) and a related technology called OFDI use light to create extremely detailed, close-up images of the artery wall.
Intravascular ultrasound (IVUS) uses sound waves to see a bit deeper into the wall structure. With these tools, doctors can now actually see the difference between a torn plaque cap with an exposed fatty core, versus an eroded plaque with an intact cap and a clot just sitting on top of a rough surface.
In the 23-year-old’s case mentioned earlier, this kind of imaging is what confirmed his heart attack was caused by erosion, not rupture.
A standard scan alone would have just shown a blocked artery, with no way to tell why.
This distinction changes how a patient gets treated. Some clots caused by erosion can be treated by suctioning out the clot and using blood-thinning medication alone, without needing a stent, because there’s no unstable fatty plaque left underneath that could tear open again. Clots caused by rupture almost always get a stent, because the damaged, inflamed plaque underneath is still a risk for forming another clot if it’s left uncovered. Getting this right isn’t just an interesting detail. It can decide whether a patient leaves the hospital with a permanent metal stent in their artery or not.
Time, Blood Flow, and Why “Time Is Muscle” Isn’t Just a Slogan
Once doctors confirm a clot is causing a heart attack, speed becomes the single most important factor in how much damage occurs. Blood flow through the artery gets scored on a scale called TIMI flow, ranging from TIMI 0 (no flow at all past the blockage) to TIMI 3 (normal, full flow restored). The whole point of clot-busting drugs and emergency stent procedures is to get blood flow back to TIMI 3 as fast as humanly possible.
Speed matters this much because heart muscle doesn’t die all at once. Damage spreads gradually, starting from the innermost layer of heart muscle and moving outward toward the surface over several hours, as that starved tissue slowly runs out of its oxygen reserves.
Getting treatment early, ideally within the first six hours of symptoms starting, can make the real difference between that muscle surviving and it turning into permanent scar tissue. This is the whole reason hospitals track something called “door-to-balloon time” as a quality measure.
But that measure only makes sense for a clot-caused heart attack. There’s no artery to reopen with a balloon in a Type 2 heart attack caused by something like severe anemia. That’s exactly why figuring out the right diagnosis matters before treatment even begins.
Side-by-Side: What Each Term Actually Means
| Coronary Thrombosis | Myocardial Infarction | |
|---|---|---|
| What it is | A clot blocking an artery in the heart | Heart muscle dying from lack of oxygen |
| How it’s confirmed | Angiogram, detailed artery imaging (OCT/IVUS), or autopsy | Blood test (troponin) plus symptoms, ECG changes, or imaging |
| Can happen without the other | Yes, most plaque cracks heal without causing lasting damage | Yes, Type 2 heart attacks and MINOCA happen with no clot at all |
| Main cause | A torn or worn plaque (behind about 75% of sudden blockages) | Any imbalance between oxygen supply and demand |
| Role in diagnosis | One possible piece of evidence for a heart attack | The overall diagnosis, with 5 official types |
Why This Difference Actually Changes Treatment
This isn’t just a technical detail for textbooks. A Type 1 heart attack, caused by a clot, gets treated by going after the clot and the damaged plaque directly: blood thinners, clot-preventing drugs, and either an emergency stent procedure or, if that’s not available fast enough, clot-dissolving medication.
The whole emergency treatment plan assumes there’s a clot sitting in the artery that needs to be cleared out.
A Type 2 heart attack or MINOCA doesn’t respond to that same approach. Putting a stent into an artery that isn’t actually blocked won’t help someone whose heart attack was caused by severe anemia or a dangerous heart rhythm. For these patients, doctors need to fix the real problem instead, whether that’s treating the anemia, correcting the heart rhythm, or managing an infection, rather than doing anything to the artery itself.
Doctors are now specifically taught to note when a suspected clot-caused heart attack has been “ruled out” after a scan shows no clot or plaque damage, so the treatment doesn’t automatically follow the wrong playbook.
Telling a Type 1 from a Type 2 heart attack early on is still described as a real challenge in emergency medicine, because they can look identical at first: same chest discomfort, same high troponin reading, even though the actual cause and the right treatment are completely different.
The Scale of the Problem
Just to put this in perspective: heart attacks affect an estimated 3 million people worldwide each year, and more than 1 million people die from one in the US alone every year. Worldwide, heart disease from clogged arteries makes up roughly 49% of the 18.6 million deaths from heart and blood vessel disease recorded in 2019, up sharply from 12.1 million such deaths back in 1990. One large 2023 review, covering data from nearly 8 million people, found that 3.8% of adults under 60 and 9.5% of adults over 60 have had a heart attack, with the risk climbing steadily as people age.
Since a clot is behind most of these cases, that’s why so much heart research today focuses on stopping plaque from cracking in the first place, on better blood-thinning drugs, and on clearing clots faster once they form. But the fact that a meaningful share of heart attacks, like MINOCA and Type 2, happen with no clot at all is exactly why doctors no longer treat “heart attack” as one single, one-size-fits-all condition.
Frequently Asked Questions
Can you have a clot in your artery without having a heart attack?
Yes. Plenty of plaque cracks and even some clots that don’t fully block the artery happen without causing enough lasting damage to count as a heart attack. The body often heals these quietly, absorbing them back into the plaque.
Can you have a heart attack without any clot at all?
Yes. Both Type 2 heart attacks and MINOCA meet the full official criteria for a heart attack without any clot ever being found.
Which one do doctors figure out first in the emergency room?
Usually the heart attack diagnosis comes first, based on symptoms, an ECG, and the troponin blood test. Whether a clot is actually there gets confirmed afterward, once doctors do a scan to figure out the underlying cause.
Is a clot more dangerous than a heart attack?
They’re not really things you can compare that way. The clot is usually the cause in a classic heart attack, while the heart attack is the actual damage that results. A bigger or longer-lasting clot usually means more muscle damage, which is exactly why getting treated fast matters so much.
Bottom Line
Coronary thrombosis is what a doctor would see if they looked inside the artery. Myocardial infarction is what gets confirmed from a blood test and an ECG. In most real-world heart attacks, one leads to the other: a plaque cracks, a clot forms on top of it, blood flow gets cut off, and the heart muscle downstream starts to die. But the official rules doctors use, with five different types of heart attack, plus conditions like MINOCA, exist precisely because that chain of events doesn’t always play out that way. Knowing the difference isn’t just a technicality. It can decide whether someone gets rushed in for an emergency stent, or gets checked for something else entirely that a stent can’t fix.
Sources
- Severity of coronary atherosclerosis at sites of plaque rupture with occlusive thrombosis, ScienceDirect
- ST-elevation myocardial infarction caused by plaque erosion in a 23-year-old male, NCBI/PMC
- Coronary Plaque Erosion: Epidemiology, Diagnosis, and Treatment, NCBI/PMC
- Fourth Universal Definition of Myocardial Infarction (2018), Circulation / AHA Journals
- Myocardial Infarction With Non-obstructive Coronary Arteries: A Clinical Conundrum, NCBI/PMC
- Role of Intracoronary Imaging in MINOCA: A Review, NCBI/PMC
- Acute Myocardial Infarction, StatPearls, NIH/NCBI Bookshelf
- Acute Myocardial Infarction Epidemiology Forecast 2026-2035, Research and Markets
- The global prevalence of myocardial infarction: a systematic review and meta-analysis, BMC Cardiovascular Disorders